
Wristbands for Patients with Dementia: Design Considerations for Wandering Prevention
Wandering is one of the most concerning behaviors associated with dementia and other forms of cognitive impairment. It affects a significant proportion of individuals living with Alzheimer's disease and related dementias, and it carries substantial risks: exposure to traffic, hypothermia, dehydration, falls, and the psychological trauma of becoming lost and disoriented. For caregivers—both professional and familial—the constant vigilance required to prevent wandering is exhausting, and no amount of supervision can guarantee that a moment of distraction will not coincide with a patient's decision to leave a safe environment.
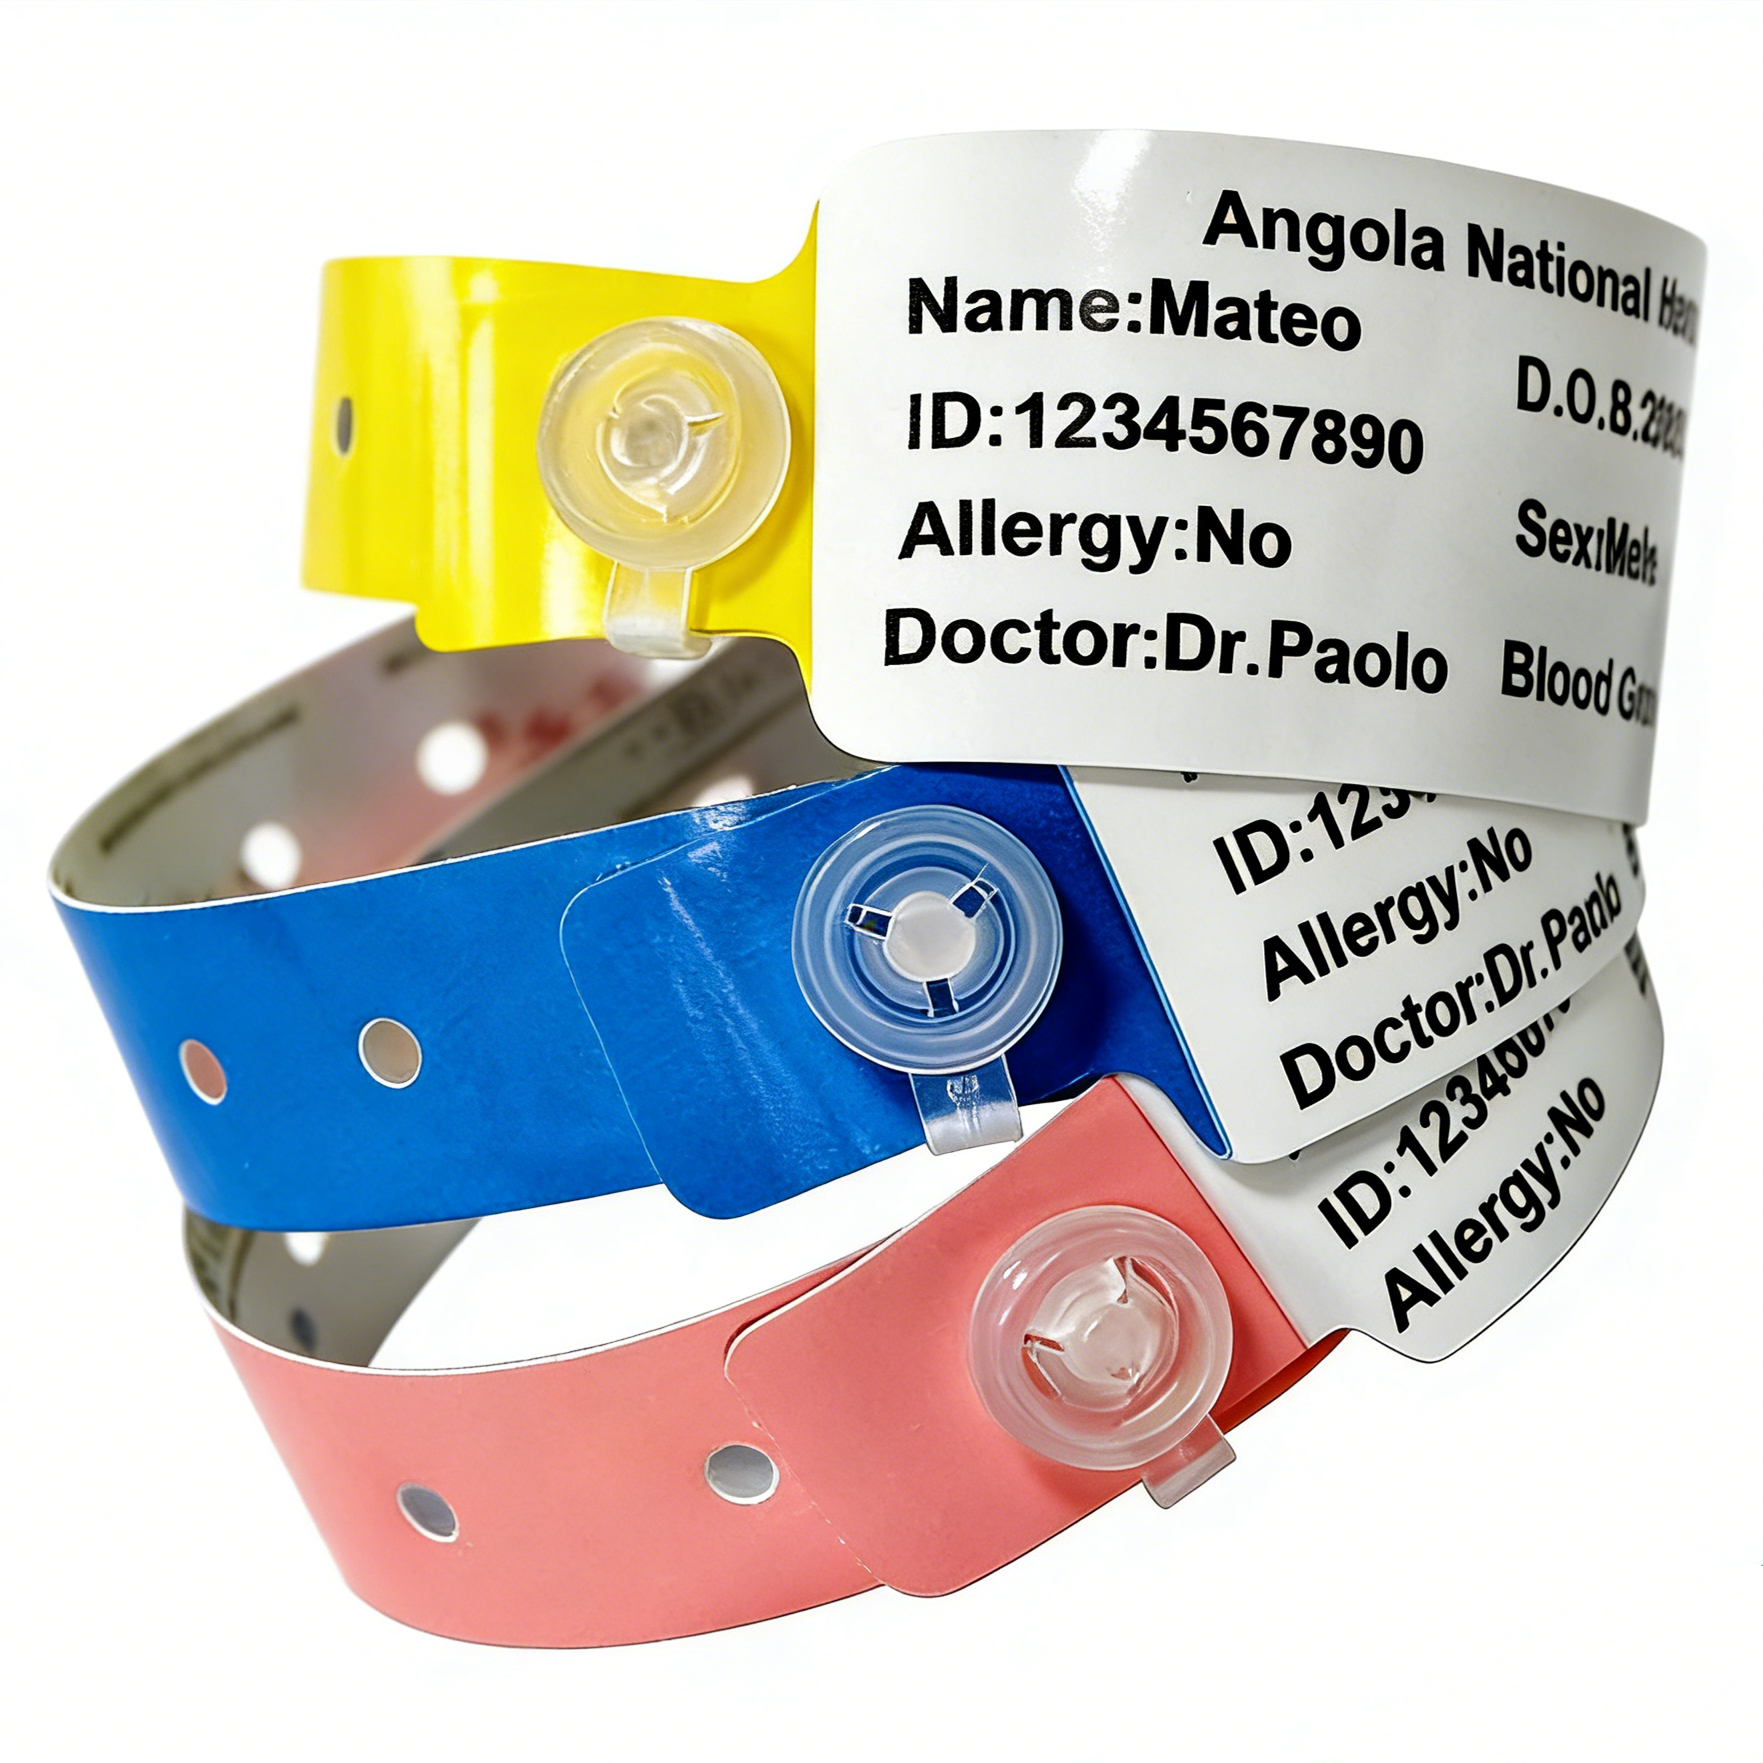
The response to this challenge has produced a range of technological and procedural solutions. Among the most widely adopted is the dementia wristband: a wearable device that can serve multiple functions, from simple visual identification to sophisticated real-time location tracking. The wandering patient wristband occupies a unique position in care practice because it operates at the intersection of safety, dignity, and personal autonomy. It is simultaneously a protective tool and a potential instrument of surveillance. How it is designed, how it is implemented, and how its ethical boundaries are negotiated determine whether it enhances care or undermines it.
This article examines the design considerations that shape effective dementia wristbands, with particular attention to three core functions: wandering prevention, patient identification, and emergency contact information delivery. It also addresses the ethical and privacy questions that arise when wearable technology is used with a population whose ability to consent is often compromised. The goal is to provide healthcare professionals, care home administrators, and family caregivers with a practical framework for selecting and deploying wristband solutions that serve patients well.

The Spectrum of Wristband Technologies
Dementia wristbands are not a single product category. They span a wide technological spectrum, from passive visual identifiers to active electronic tracking systems. Understanding this spectrum is essential to matching the right solution to the right patient and care environment.
Passive Visual Identifiers. At the simplest end are color-coded or printed wristbands that carry no electronic components. These bands serve purely as visual flags: a blue band with a forget-me-not flower, for example, signals to hospital staff that a patient has dementia and may need extra help with communication or orientation. Such bands do not prevent wandering directly, but they facilitate early recognition of a patient's needs and enable staff to intervene appropriately. Their advantages are simplicity, low cost, and zero privacy implications beyond the visible disclosure of a diagnosis. Their limitation is that they provide no location information and no ability to alert anyone if the wearer leaves a safe area.
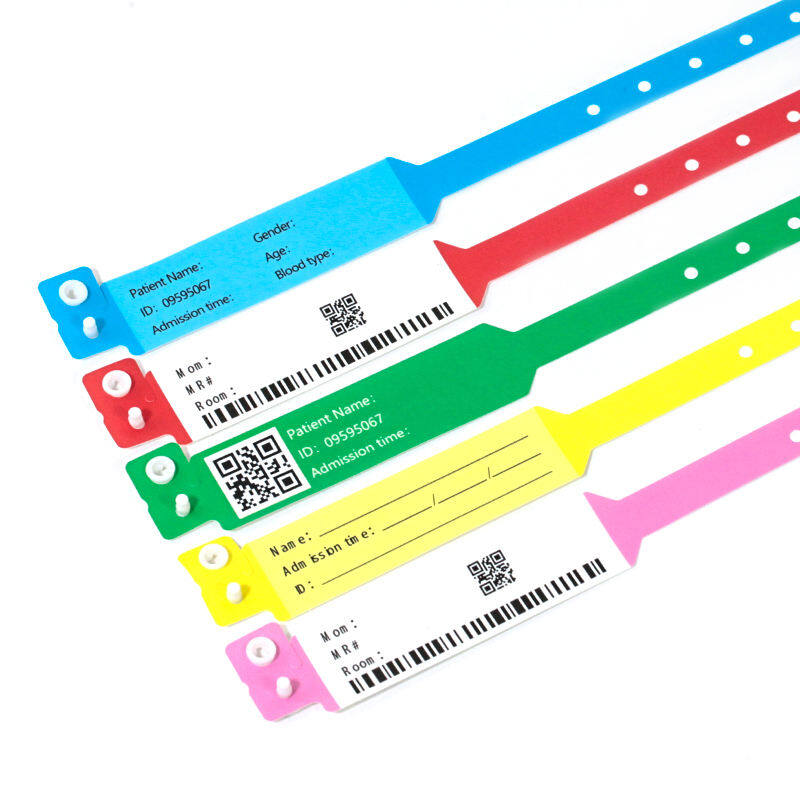
NFC-Enabled Identification Wristbands. A middle-ground option uses Near Field Communication (NFC) technology embedded in the wristband. These bands contain a passive chip that stores emergency contact information and, in some implementations, medical details. When a first responder, a member of the public, or a care worker scans the band with an NFC-enabled smartphone, the stored information appears on the phone screen. The Cambridgeshire Dementia Safeguarding Scheme exemplifies this model: it issues yellow wristbands that allow anyone who finds a lost individual to access next-of-kin contact details by tapping their phone against the band. Crucially, these bands do not continuously transmit location data, do not require batteries, and do not track movement. They activate only when deliberately scanned, which makes them a privacy-preserving option for community-dwelling individuals at risk of becoming lost.
Active RFID and Real-Time Location Systems. At the most technologically sophisticated end are active RFID tags and Real-Time Location System (RTLS) bracelets. These devices use radio frequency communication to enable continuous or near-continuous monitoring of a wearer's location within a facility. Bluetooth Low Energy (BLE) wristbands, for example, can trigger a geofencing alert when a patient leaves a designated area, setting off an alarm on the nursing station dashboard and simultaneously notifying on-duty nurses. More advanced systems combine BLE, Wi-Fi, UWB, or hybrid RTLS technologies to achieve room-level positioning, individualized safety permissions, and full-facility event analytics. Patient-worn devices are increasingly moving toward smaller, more discreet, waterproof, and tamper-resistant designs to improve wearer acceptance and preserve dignity.

Each of these technology tiers serves different needs and raises different design considerations. The remainder of this article examines the key dimensions along which these solutions must be evaluated.
Design Consideration One: Wandering Prevention Efficacy
The most fundamental question for any wandering patient wristband is whether it actually prevents wandering. The evidence base is mixed, and the answer depends heavily on the technology type and the care environment.
Facility-Based RTLS: Strong Theoretical Case, Uneven Evidence. RTLS systems are designed to detect when a tagged individual approaches a monitored exit, allowing staff to intervene before the person leaves the facility. The logic is compelling: a bracelet that triggers an alert at the doorway gives staff the opportunity to redirect the patient, potentially preventing an elopement. In practice, however, the effectiveness of these systems depends on factors that are not always present: adequate staffing to respond to alerts in a timely manner, appropriate configuration of alert thresholds to avoid alarm fatigue, and integration with door hardware that can physically delay exit if necessary.
Research on RTLS in long-term care settings has found that while these systems are promoted as improving safety, their real-world benefits are less clear. Staff in one study reported that it was often simpler to locate residents in person than to monitor the RTLS dashboard continuously, and that they lacked the time and resources to respond to alerts in real time. This finding suggests that RTLS wandering prevention is not a substitute for adequate staffing and attentive care; it is a supplement that works only when the human response system is already in place.
Community-Based NFC: Reunion Rather Than Prevention. For individuals living in their own homes or in assisted living settings without perimeter security, the wandering risk is different. There is no monitored exit to secure, and the person may leave the home without anyone noticing. In this context, the wristband's role shifts from prevention to reunion: it enables a lost individual to be identified and returned to safety quickly. The NFC wristband model, combined with the Herbert Protocol (a UK initiative that encourages families to compile key information about a person with dementia for police use in search operations), provides a practical layered approach. The wristband serves as the immediate identification tool; the Herbert Protocol provides the background information that guides a search if the person goes missing.
The Limits of Any Wristband. It is important to be candid about what wristbands cannot do. A wristband cannot prevent a determined individual from leaving if they are not intercepted. It cannot function if the wearer removes it. It cannot replace the vigilance of caregivers or the safety features of the built environment. The most effective wandering prevention strategies combine multiple layers: wristband technology, door alarms and secured exits in facilities, GPS or community alert systems for individuals at higher risk, and, most importantly, care practices that address the underlying reasons for wandering—boredom, anxiety, restlessness, or the need for purposeful activity.

Design Consideration Two: Identification and Emergency Contact Information
Beyond preventing wandering, dementia wristbands serve a critical identification function. When an individual with cognitive impairment becomes lost or is found in a confused state, the wristband may be the only reliable source of information about who they are and whom to contact.
The Problem of the Unidentified Patient. In emergency medicine, unidentified patients present significant challenges. Without a name, medical record number, or contact information, clinicians cannot access medical history, cannot verify allergies or medications, and cannot notify family. For patients with dementia, the problem is compounded because they may be unable to communicate their own identity. A wristband that carries this information transforms an unidentified patient into an identifiable one, enabling appropriate care and facilitating reunion with caregivers.
What Information Should Be Carried. The information load of a dementia wristband should be calibrated to the wristband's technology and the context in which it will be used. For NFC-enabled community wristbands, the essential information includes: the wearer's first name, a nominated emergency contact's name and phone number, and possibly a brief note indicating that the wearer has dementia and may be disoriented. For facility-based wristbands, the information may include the resident's full name, unit and room number, and care directives relevant to wandering risk. For medical ID bracelets that incorporate QR codes or NFC, additional medical information—diagnoses, medications, allergies, physician contact—can be stored and accessed in an emergency.

The key design principle is precision over volume. Information that is difficult to read, requires a special app, or contains too much detail may slow down a first responder rather than help them. The most effective wristbands present a small set of clearly prioritized information in a format that is immediately accessible.
Legibility and Durability. Whether the information is printed directly on the band or stored electronically, it must survive the conditions of daily wear. Printed text must remain legible after exposure to moisture, friction, and cleaning agents. Electronic components must be sealed against water and dust. The XTAG Patient Tag and similar products carry IP67 ratings, meaning they are waterproof and dust-tight. NFC chips are typically embedded in waterproof materials that can be worn during bathing and other daily activities. Durability is not a minor consideration: a wristband that fails after a few weeks is worse than no wristband at all, because it creates a false sense of security.
Design Consideration Three: Comfort, Wearability, and Dignity
For any wristband to serve its purpose, the wearer must actually wear it. This seems obvious, but it is a design challenge that many products fail. People with dementia may remove items that are uncomfortable, unfamiliar, or stigmatizing. A wristband that is heavy, irritating, or aesthetically intrusive is likely to be discarded, rendering its safety functions moot.

Weight and Form Factor. The most effective dementia wristbands are lightweight and unobtrusive. Products are increasingly designed with low-profile forms that are non-stigmatizing and blend into daily life. The Cambridgeshire wristband, for example, is described as looking similar to a watch, a familiar form factor that carries no stigma. In contrast, bulky devices that resemble prison ankle monitors or medical restraints are more likely to be resisted and removed.
Comfort for Long-Term Wear. Because dementia wristbands are typically worn continuously—24 hours a day, seven days a week—comfort is paramount. Materials should be hypoallergenic, breathable, and smooth-edged to prevent skin irritation. The band should be adjustable to fit a range of wrist sizes without being either too tight (causing pressure marks and restricting circulation) or too loose (allowing the band to slide off or become caught on objects). Recent procurement specifications for medical-grade patient wristbands explicitly require wearable materials that are gentle and suitable for long-term wear on elderly skin.
Tamper Resistance vs. Wearer Control. There is an inherent tension between tamper resistance and wearer autonomy. A tamper-evident band that triggers an alert when cut or removed can prevent a confused individual from discarding their identification, but it also removes their ability to remove a device they find uncomfortable or distressing. Recent procurement specifications for high-risk patient wristbands include medical anti-tamper structure that triggers an alarm upon forced removal, alongside anti-detachment accessories for agitated patients. These features are appropriate for high-risk individuals in secured facilities, but they raise ethical questions when applied to individuals in community settings who have the legal capacity to make decisions about their own care. Designers and care providers must consider whether the safety benefit of tamper resistance justifies the restriction on personal autonomy, and this consideration should be documented and revisited over time.
The story of one Chinese police officer illustrates this tension vividly. His father, diagnosed with Alzheimer's disease, repeatedly removed his location wristband, identity tags, and tracking devices. The officer recalled: It looked like an electronic shackle. The identity tag openly declared I am sick, please help me. He would quietly remove it, throw it on the roadside, and come home with a calm face, as if nothing had happened. The father did not want others to know he was ill; he felt it was causing trouble for people. The solution was not to force the device on him, but to design a garment with a hidden pocket for the tracker—allowing the father to go out with dignity while still being protected.
The Ethical and Privacy Landscape
No discussion of dementia wristbands is complete without addressing the ethical questions they raise. These questions are not abstract; they have direct implications for how wristbands are designed, implemented, and evaluated.
Consent and Assent. Many individuals with dementia lack the legal capacity to provide informed consent for the use of tracking technology. In these cases, consent is typically provided by a substitute decision-maker—a family member, a legal guardian, or a designated healthcare proxy. However, ethical practice requires more than a signature on a consent form. It requires ongoing attention to the wearer's preferences and responses. If a resident shows signs of distress, repeatedly attempts to remove the wristband, or verbally objects to wearing it, these signals should be treated as meaningful communication about their wishes, not as compliance challenges to be overcome. Research on technology-supported care in nursing homes emphasizes that ethical review procedures typically require informed consent from participants or their legal representatives when residents have limited decision-making capacity, with data anonymized and handled confidentially.

The Expansion of Surveillance. RTLS and other continuous tracking technologies represent a qualitatively different form of monitoring than cameras in public areas or door alarms. They extend surveillance into private spaces—bedrooms, bathrooms—and collect data about an individual's movements throughout the day and night. This data may have no direct clinical relevance, yet it captures intimate details of a person's daily life. Care organizations have an obligation to be transparent about what data is collected, how it is stored, who has access to it, and how it will be used. The principle of data minimization—collecting only what is necessary for the stated purpose—should guide system configuration. Research on privacy concerns in continuous monitoring explicitly identifies privacy concerns related to continuous monitoring as a recognized risk in clinical studies.
Dignity and Stigma. Some family members and care professionals have expressed concerns that visible identification—whether a wristband or a bedside sign—may expose a person to stigma or discrimination. These concerns are not unfounded. Dementia carries significant social stigma, and a visible marker of diagnosis can shape how others perceive and treat the wearer. Design choices can mitigate this risk: a wristband that looks like a watch, a medical ID bracelet, or a piece of jewelry is less stigmatizing than one that resembles a hospital identification band or a tracking device. The market is responding to this awareness, with patient-worn devices moving toward smaller, more discreet, waterproof, and tamper-resistant designs to improve wearer acceptance and preserve dignity.
Balancing Beneficence and Autonomy. The ethical framework that should guide dementia wristband implementation is one of relational ethics: recognizing that decisions about tracking technology affect not only the individual wearer but also their family, caregivers, and the broader care community. Safety is a legitimate goal, but it should not be pursued at the expense of all other values. The question is not Can we track this person? but Should we track this person, and if so, under what conditions and with what safeguards? Research on person-centeredness in long-term care identifies safety versus freedom as one of six inherent tensions impacting person-centered practice, noting that this tension is interconnected with other domains and often manifests throughout the resident experience. This question deserves explicit, documented consideration, not a default assumption that safety always wins.
The guidance from Hong Kong's Elderly Health Service is instructive here: relying solely on restraint or restriction not only fails to solve the problem but can also anger patients, damage the caregiver relationship, and accelerate physical and cognitive decline. The recommended approach is to understand the reasons for wandering—whether the person needs the toilet, is looking for food, is bored, or is disoriented—and to address those needs through environmental design, meaningful activity, and appropriate assistive devices.
Practical Recommendations for Care Providers
Drawing on the design considerations and ethical analysis above, the following recommendations can guide care organizations and families in selecting and implementing dementia wristbands.
Match the technology to the risk profile and setting. An individual living independently in the community with mild cognitive impairment may benefit most from a simple NFC identification bracelet combined with the Herbert Protocol. A resident of a secure memory care unit with a history of elopement attempts may require an RTLS system with geofencing and door integration. A procurement specification for a Chinese elderly care center illustrates the range of features that may be considered: medical anti-tamper structure, SOS one-button call, IP67 waterproofing, low battery alerts, offline alerts, and vital sign monitoring for heart rate, temperature, and step count. There is no one-size-fits-all solution; the choice should be informed by an individualized risk assessment.
Prioritize comfort and non-stigmatizing design. The best wristband is the one the wearer will actually wear. Choose lightweight, comfortable materials. Opt for designs that look like familiar objects (watches, medical ID bracelets) rather than institutional devices. Test the fit and comfort with the wearer before committing to a long-term solution. As one caregiver's experience demonstrated, if the elder is not comfortable, they will not keep wearing it; and if they don't wear it, no matter how accurate the locator is, it's useless.
Be transparent about capabilities and limitations. Before implementing a tracking system, ensure that residents (to the extent possible), families, and staff understand what the technology can and cannot do. NFC wristbands, for example, do not track location and provide no wandering prevention; they only enable identification after the person has been found. RTLS systems can alert staff to exit attempts, but they depend on staff availability to respond. Misunderstandings about capabilities can lead to unrealistic expectations and inadequate safety planning.
Establish continuous consent processes. For individuals who cannot provide informed consent, involve substitute decision-makers, but do not treat their consent as a one-time event. Revisit the decision periodically. Attend to the wearer's behavioral cues—resistance, distress, removal attempts—as meaningful data about their preferences. The person-centered practice literature emphasizes that involving residents in their own care decisions, to the extent possible, is a core component of quality dementia care.
Develop clear policies on data governance. Specify what data is collected, where it is stored, who can access it, and how long it is retained. Use role-based access controls and audit trails to prevent unauthorized use. Be transparent with residents and families about these policies. A comprehensive procurement specification for a care center platform, for example, includes requirements for complete log auditing of location records, alarm events, and device operation logs, with support for query and export to meet security and quality control audit requirements.
Evaluate outcomes, not just implementation. The ultimate measure of a wristband program is not whether residents are wearing bands, but whether the program reduces wandering incidents, improves response times when wandering occurs, and enhances—or at minimum does not diminish—quality of life. Collect data on these outcomes and use it to refine the program. The experience of some nursing homes in discontinuing technology due to limited financial sustainability and absence of demonstrated workload reduction serves as a cautionary reminder that implementation alone is not sufficient.
Conclusion
The dementia wristband is a deceptively simple object. A band of material worn on the wrist, carrying a name or a chip or a transmitter—it seems to offer a straightforward solution to a complex problem. But as this article has shown, the design and implementation of effective wristbands for wandering prevention require careful navigation of technical, clinical, and ethical considerations.
The most successful approaches will be those that treat the wristband not as a standalone intervention but as one component of a comprehensive care strategy. They will prioritize the comfort and dignity of the wearer, recognizing that a wristband that is removed and discarded protects no one. They will be transparent about capabilities and limitations, avoiding the trap of technological solutionism. And they will remain attentive to the ethical questions that arise when safety and autonomy, protection and privacy, come into tension.
For people living with dementia and those who care for them, the wandering wristband can be a valuable tool. But it is a tool that must be wielded thoughtfully—with humility about what technology can achieve, and with unwavering respect for the person who wears it.
Continue Reading
Have Questions About Wristbands?
Our team is ready to help you find the perfect wristband solution for your needs. Contact us directly on WhatsApp for quick responses.
Contact on WhatsApp